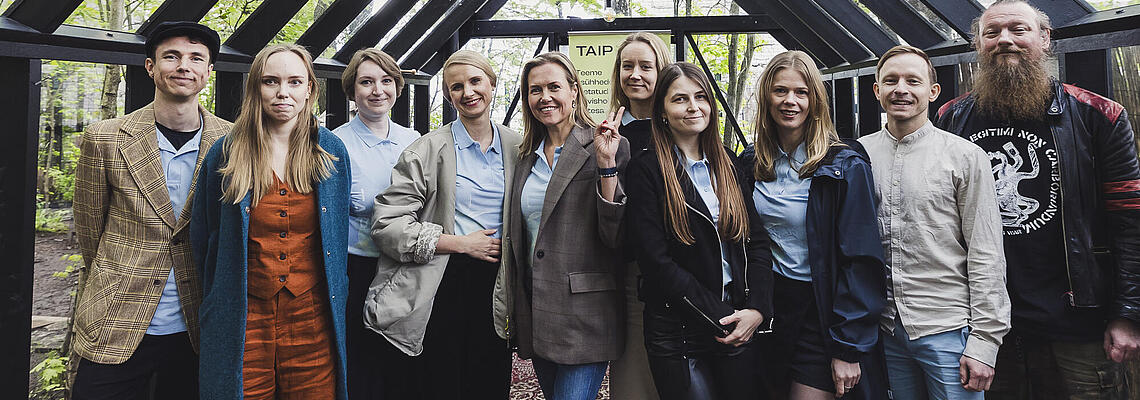Wir haben festgestellt, dass ihre bevorzugte Sprache Deutsch ist. Klicken Sie hier, um zur deutschen Version dieser Seite zu gelangen.
We have noticed that your preferred language is English. Click here to access the English version of this page.
Shopping cart
Small country, short distances, smart people: how Estonia is building psychedelic therapy from the policy end
Dr. sc. hum. Henrik Jungaberle Oliver Berg Cristina Kroon
The Estonian foundation TAIP is two years old, has met most of its country's parliamentary parties, and currently supports two participants in the MIND Foundation's ninth APT cohort through co-funded scholarships
Henrik Jungaberle in conversation with Oliver Berg and Cristina Kroon representing TAIP
This is the long read. A short read, a condensed version of this article, is published on the MIND Foundation's LinkedIn page. A table at the end of the article explains the abbreviations used.
Why we are starting the European Ecosystem Series
The MIND Foundation turns ten this year, and a tenth birthday changes your field of vision: you stop focusing only on what you have built and start noticing who has built alongside you, sometimes with you, sometimes inspired by you, and often inspiring you in return. Over the past decade a novel European landscape of organizations has emerged that want psychedelic therapy to arrive in public health systems rather than in private niches. Like the MIND Foundation, they work on and follow a different value system than a whole generation of psychedelic advocacy before them: evidence before conviction, health systems before subcultures, patients before molecules. Some drew inspiration from organizations like the MIND Foundation, and we have learned, and keep learning, from several of them. Few are well known outside their own country.
This series is about those organizations, European collaboration, and about a question that the North American debate, shaped by one comparatively uniform market, has not had to answer: how does a treatment become part of a health system when there is no single agency, no single market, and no single language? In the United States, the question of who may deliver psychedelic therapy was put to a federal docket this September, when the FDA held a public hearing on the future therapeutic use of psychedelic drugs and asked, among other things, on what evidence training curricula should rest and which expert bodies should endorse them (U.S. Food and Drug Administration, 2026a, 2026b). In Europe, that question has no single address. It is answered twenty-seven times, in twenty-seven health systems, by professional associations, ministries, parliaments, and the civic organizations that connect them. That is not per se a weakness of the European way, but it may become one if it keeps companies with approved molecules from entering the European market. Unity in diversity is the European way, but it deserves to be described from the inside.
Each part of the series has the same shape: we visit one organization, describe its country and its people, and let them speak for themselves in passages headed "In their own words". The questions are the ones we asked; the answers are theirs, edited for length and reviewed by them before publication. Around those passages we add what an outside observer can see and the people inside cannot say. We begin with the smallest country and, in some respects, the fastest mover: Estonia.
A country where everyone is a quick visit away
Estonia has 1.36 million inhabitants (Statistics Estonia, 2026). Its parliament, the Riigikogu, has 101 seats; the next election is on March 7, 2027 (Estonian National Electoral Committee, 2026). When I mentioned in our interview that the German Bundestag has 630 members and is very hard to reach, Oliver Berg, the executive director of TAIP, replied: "One of the specifics of Estonia is related to our being small. The distance to policymakers is a lot shorter than in a big country like France or Germany."
TAIP, in full Sihtasutus Teraapia Arenduseks ja Innovatsiooniks Psühhedeelikumidega, the Foundation for Therapeutic Advancement and Innovation with Psychedelics, was registered in Tallinn in May 2024 after a year in which its three founders did nothing but design it (TAIP, n.d.-a). Berg is the organizer among them. He came to the subject from two directions at once: a lived experience of depression that antidepressants did not make better, and a master's degree in Amsterdam, where he studied the political history of psychedelics and wrote his thesis on what the ongoing psychedelic renaissance means for EU drug policy, and on a gap he had noticed. "We have a growing body of scientific evidence showing the potential of these medicines, and we have a political reality that still ignores it." His conclusion was not a call for more research but for a different kind of institution: a civic organization that carries the message of scientists and psychiatrists to decision-makers, because the scientists and psychiatrists are too busy doing their work. The second founder is Viljar Veede, a psychiatrist who built Estonia's first systematic ketamine treatment service between 2021 and 2024 and who chairs TAIP's supervisory board (TAIP, n.d.-b; ERR News, 2025). The third founder is Mari Salla, who brings a background in social work and family therapy. Cristina Kroon, a neuroscientist with a doctorate in medical neuroscience from Charité in Berlin, joined a year later and now leads TAIP's policy and strategy work alongside her position as innovation scout at the medical faculty of the University of Tartu.
In their own words: starting a foundation in a country of 1.36 million
Henrik Jungaberle: How did you find each other?
Oliver Berg: When I came back to Estonia from the Netherlands, I looked around for an organization like that. There was a very small NGO, but it had no ambition to create change. Estonia is effectively one city, so you find people fast. That is how I found Viljar Veede, the psychiatrist who had started the IV ketamine program here and had been talking about the medical potential of psychedelics in podcasts. I brought him my motivation and one idea: perhaps it is time to build what exists elsewhere in Europe, MIND Foundation in Germany, OPEN Foundation in the Netherlands. A role model was there, and Viljar was on board. We met the third founder in the summer of 2023, formed the foundation in May 2024, and early on also got to know PAREA, whose political perspective helped us decide what we would do and what we would not.
Henrik Jungaberle: Cristina, when did you come in, and was it you who found them or the other way around?
Cristina Kroon: I wrote to Oliver, about two years ago; they had been going for almost a year. I am a neuroscience PhD from Charité, and my only prior exposure was a journal club during my doctorate. When I moved to Estonia it was a huge career change, and I ended up in a job I absolutely hated. Then I saw a call in a research newsletter that some people were exploring psychedelics as medicine in Estonia, and I thought I should see if they needed a neuroscientist. I had no agenda and no personal need other than intellectual curiosity. I was looking for something that would feel meaningful, and I truly found it. It is remarkable what you can do with a very small team of highly motivated, highly competent people. Not everybody needs to be a neuroscientist or a doctor.
Henrik Jungaberle: Is there a concept behind that completeness? What is useful in the Estonian context when you present yourselves to the public?
Cristina Kroon: You absolutely need doctors on board, because our starting point is unmet clinical need, and only doctors can inform that. I started as a scientific advisor and moved into a policy lead role: how do we implement these medicines in our healthcare system? In my day job I spin technologies out of the University of Tartu's medical faculty; integrating psychedelics into the medical system sits at the very end of the same pipeline. It is about how new medicines reach patients.
Oliver Berg: The core competencies we needed from the beginning were psychiatrists and knowledge of the law. On the supervisory board we have two psychiatrists, Viljar Veede as chairman among them, an attorney and a drug policy activist with two decades of experience; in the team, a clinical psychologist. And to be transparent: from the outside it might look as if we have more resources than we actually have. A private philanthropist makes a huge difference, but all in all it amounts to about three and a half full-time positions, divided in small portions among the team.
Henrik Jungaberle: I ask this everywhere, because I know the enormous spectrum of people who approach a psychedelic organization. Do you see them in Estonia?
Cristina Kroon: It is a field that draws each individual for specific reasons, and Oliver probably gets those special applications regularly. But he has formed a team in which around half the people have no prior experience with the substances at all. To me that is the most amazing thing: people who have no idea what the experience is like, but who see the evidence and say, I want to work with this. You don't have to be an insider of the subculture to see the medical value in something. That is the beauty of science: your opinion doesn't matter, data matters. And it keeps us from getting lost in the bubble, thanks to people who are not sold on the idea that psychedelics will save the whole world.
Oliver Berg: Here, as everywhere, there is an underground community. We have talked with them to explain why we do what we do, and there could be another organization that represents that voice. But that is not our approach. We are not stuck in the psychedelic bubble.
Berlin, Tallinn, and the bubble
I recognized this immediately, because it is the staffing principle we intended to follow at the MIND Foundation from the first day, though we did not always manage it. Generally, we are seeking people in and around the organization who are not ideologized by their own experience. People who don't feel they found the final truth and start their private religion. Berlin makes that harder than Tallinn. Here the psychedelic scene is several scenes at once: party culture, underground therapists, and a fast-growing scene of business consultants, all with their own infighting. A science organization must hold its position among them. Some in the underground call this an outside view and say it's inauthentic. We do not think that context-adequate speaking and role reflexivity are inauthentic. It is how society works, and TAIP reached the same conclusion two years in, with a fraction of the noise.
From drug policy to health policy
The most instructive mistake TAIP made was to accept the desk it was assigned to. Because psychedelics are scheduled substances, the Ministry of Social Affairs routed the new foundation to its drug policy officer. "We want to talk about healthcare," Berg says, "but in the beginning we had not been assigned to the people responsible for healthcare. So part of our mission is to reshape the discourse from drug policy to healthcare." Even the founding document had to make that move. The first draft of TAIP's purpose was to integrate psychedelics into Estonian society; the notary declined to register it. The version that stands is narrower and, in practice, stronger: ensuring patients' access to psychedelic medicines. Unmet clinical need became the center point, and it quickly changed whom the foundation talks to. A member of the Estonian Psychiatric Association's board, Anne Kleinberg, MD, will open TAIP's first international conference in October and has become what Berg calls a cautious ally.. The association as a whole has not taken a position on psychedelic therapies; most of its board, in Berg's words, is still carefully curious.
The need is not abstract. Estonia's suicide rate, 14.5 deaths per 100,000 inhabitants in 2022, is the fifth highest in the European Union (Eurostat, n.d.), and the OECD puts the cost of mental ill-health at 2.8 percent of GDP a year (OECD, 2025); in the OECD's 2021 benchmark of mental health systems, Estonia's spending on mental health ranked among the lowest of the countries compared (OECD, 2021, pp. 200–201). According to the European Union Drugs Agency (EUDA), 4.4 percent of Estonians aged 15 to 34 used MDMA in the past year, the third-highest figure in the EU (European Union Drugs Agency, 2026). How a foundation with three and a half positions works with these facts is best heard from the two people who do it.
In their own words: what Estonia does differently
Henrik Jungaberle: Are there factors specific to Estonia that make your challenges different from those of your neighbors, or from the MIND Foundation's?
Cristina Kroon: There is almost no research done in this area in Estonia, so we cannot fall back on our own science. The Nordic foundations, in Finland, Sweden, Norway, are organized around early-career researchers and psychologists; they are academic and can start clinical studies. We have perhaps three scientists doing something related. We don't have that luxury, so we focused on what we can achieve with the team we have, and that is policy work. We are focused on implementation, and we try to shift the conversation: what evidence are you still missing? Or should we start implementing, look at feasibility, and get these treatments to patients? Estonia is not as open-minded as Berlin, and we expected a lot of friction. Surprisingly, the friction has been lower than we anticipated.
Henrik Jungaberle: How come?
Cristina Kroon: It depends on whom you talk to. Being assigned to drug policy experts was a mistake we made as a young organization. Knowing what I know now, I would push back: respectfully, you don't know what you are talking about; let us tell you what the field is about, and then assign us to the right department. Policymakers are cautious, and that is probably okay. But people who deal with mental health patients every day lack options for them, and that conversation is different. At the end of this summer we also met the political parties, four of them so far, because the elections are coming up in March. We went to the parliament twice in one week, and we were very positively surprised how well received we were. They see that mental health is no longer something you can sweep under the carpet. The real test is whether they act on it.
Henrik Jungaberle: How many people sit in your parliament?
Oliver Berg: 101. The distance to policymakers is a lot shorter than in France or Germany. The friction point right now is that Estonia has a downsized public sector: officials are overburdened, replies are delayed, and new initiatives may not fit on the table. Because of the security situation the budget goes to defense, and we are not investing in mental healthcare as much as the problem requires. While our suicide rate is number five in the EU, in mental-health investment we are in the bottom five of the 38 OECD countries.
Henrik Jungaberle: How much of that is inherited from Soviet times? The opioids, the drinking – does it play a role in your work?
Cristina Kroon: Alcoholism and the opioid crisis are huge public health issues, and we don't deal with them seriously enough. But there is a bottleneck that is probably universal: "who is responsible for what?". Ministries and politicians want direct asks from psychiatrists, and psychiatrists are extremely overloaded; now we expect them to be spokespersons as well. That is a gap TAIP helps to fill: we have psychiatrists on our supervisory board, and we add spokespersons who are not doctors. Ultimately, though, we need the psychiatric association to speak as an organization, not only individual members.
Oliver Berg: The historical background has an effect that is hard to reflect on within this society, because we lived fifty years under a totalitarian regime. It goes deep into how we take care of our public space, our state. And there is a generational gap. The EUDA just released its data on MDMA use among young people, and Estonia is third in the EU. But people who spent their youth in Soviet times, and who may now hold established positions in the system, have no idea what MDMA or psilocybin is, let alone what these substances could become. The psychiatrists who are aware tend to go into private practice, because there they can work with ketamine; others have not followed the studies of the last ten years. Bringing these sides together is one of the challenges.
Henrik Jungaberle: How is Estonia doing in the ketamine treatment space?
Cristina Kroon: On the esketamine front things are quiet: it is a third- or fourth-line option, expensive, and we don't know how many patients make it there. Ketamine-assisted psychotherapy is offered by one person, Viljar Veede. We are literally talking about one single individual. But in the next few months we will probably see at least two more clinics open, and people from these clinics are coming to MIND or are in training. Our scholarships have really motivated this widening of options for Estonian patients.
Implementation first
That last answer is where the story turns toward Berlin, and it carries the difference that struck me most. The Nordic foundations grew out of universities and are organized around trials; TAIP, with no research base of its own, put implementation first. Its question, what evidence are you still missing, is one we in Germany, with our own large trials behind us, should hear more often. Two years of policy work and a handful of co-funded training places have helped to produce something a phase 3 trial cannot: a second and a third clinic in a country that had one.
Europe's gatekeepers: EMA, HTA requirements, and where the money is
There is a second reason this blog series is needed, and it has to do with where the money and the attention are. By my estimate, about 90 percent of the attention of small and big pharma in this field is currently bound in the United States, where expected FDA approval opens a market that alone accounted for 53 percent of the world's pharmaceutical sales in 2024; Germany, Europe's largest market, stood below five percent (Gründer et al., 2026). Companies behave accordingly. Every phase 3 trial with a psychedelic that was running in November 2025 tested the drug against placebo, not one against an established treatment, and none of their sponsors had applied for the EMA's PRIME scheme, the European counterpart of the FDA's breakthrough designation (Gründer et al., 2026). The exception confirms the pattern. In February 2026 the EMA granted PRIME eligibility to bretisilocin, a short-acting 5-HT2A agonist in phase 2 for major depressive disorder and, as far as we can tell, the first psychedelic compound in the scheme (European Medicines Agency, 2026). The applicant was not a psychedelic start-up but AbbVie, which had bought the program from Gilgamesh Pharmaceuticals in 2025 for up to 1.2 billion dollars (AbbVie, 2025). Europe gets attention when a company can afford two continents at once. For everyone else: first the American market; everything else comes later.
That does not mean Europe is idle. The European Medicines Agency convened a two-day multi-stakeholder workshop in April 2024 to work toward an EU regulatory framework for psychedelics and published the report and the presentations (European Medicines Agency, 2024). Its revised guideline on clinical trials in depression, in force since September 30, 2025, contains a dedicated section on psychedelics: on blinding, on standardizing psychological support, on safety monitoring, and on the agency's position that psychedelics should not, for now, be tested as first-line treatments (European Medicines Agency, 2025). EMA scientists had laid out the regulatory perspective in The Lancet two years earlier (Butlen-Ducuing et al., 2023). Approval in Europe, in other words, has a roadmap.
Approval, however, is not access. In Europe the harder hurdle comes afterward, when health technology assessment (HTA) bodies decide whether a new treatment offers added benefit over the existing standard, and therefore whether public insurers will pay for it. Gerhard Gründer, Andreas Meyer-Lindenberg, colleagues at the Central Institute of Mental Health (ZI) in Mannheim and I have described this pathway in European Neuropsychopharmacology (Gründer et al., 2026), and the lesson of esketamine is the lesson for psychedelics: approved in 2019, the nasal spray was denied any added benefit in Germany, France, and Britain because it had never been compared with a relevant alternative. Only a later trial against quetiapine, with a 32-week follow-up, led the German Federal Joint Committee (G-BA) in 2023 to recognize a hint of considerable additional benefit, the first such verdict for a drug against a mental illness in Germany. There are not twenty-seven equally weighty HTA agencies in Europe. A few set the tone: Germany's IQWiG and Federal Joint Committee, France's HAS, and, outside the EU, Britain's NICE, followed by the agencies of Spain, Italy, the Netherlands, and Sweden. Most smaller member states orient their decisions on these, and since January 2025 the EU's HTA Regulation has begun pooling the clinical part of the assessment into joint clinical assessments, so that member states can rely on a single appraisal (Gründer et al., 2026). For a country like Estonia this is decisive: what Germany's IQWiG and France's HAS conclude about psilocybin will co-shape what Estonia can reimburse.
This is why we consider an HTA-grade study a European task, not a German one. It would test psilocybin-augmented psychotherapy against the guideline standard for patients who did not respond to a first antidepressant, augmentation with psychotherapy in both arms, and follow them for at least six months. To our knowledge, no company is currently planning such a trial, although discussions are under way. Under the leadership of Gerhard Gründer, the MIND Foundation and its partners already have a protocol for it that has been reviewed by Germany's Federal Institute for Drugs and Medical Devices (BfArM). What is missing is a financing and collaboration model, and here the cooperation between countries and companies that the paper calls for becomes concrete. We are open to running this study in Germany, Europe's most important market, together with a manufacturer, and to taking other countries along: as trial sites, as sources of patients and clinicians, and as co-owners of the data. Once the American market is won, companies will need European evidence; the organizations in this series are the ones who can produce it with them, and they can be credible links to society, paving the way for acceptance and best practice.
Germany has already shown what a model looks like. On July 11, 2025, BfArM approved a compassionate use program for psilocybin in treatment-resistant depression, the first time a psychedelic became available to patients under expanded-access legislation in the EU (Gründer et al., 2025). Treatment follows the protocol of the EPIsoDE trial and is delivered at two sites: the ZI in Mannheim and OVID Clinics in Berlin, currently the only private provider with a compassionate use license. The license is held by Gerhard Gründer, who implements the program both at his chair at the ZI and at OVID Clinics, where he is chief physician and one of the CEOs (Gründer et al., 2025). Every dosing session is accompanied by two trained therapists, a patient board of former trial participants advises the program, and public health insurance largely covers the costs. Unlike the Swiss program, which authorizes access case by case, the German program needs no individual patient-level approval, and it is not restricted to German residents: patients from other European countries and beyond can be treated. Both sites collect safety, efficacy, and contextual data in a harmonized way, because a program like this is worth as much as what it teaches. That is the body of experience Europe needs, and it is open to Estonia's patients today and to Estonia's clinicians as soon as they are trained. The Czech Republic plans a national scheme from 2026 (Gründer et al., 2025); the more countries connect their programs, the sooner Europe has real-world evidence of its own.
Where the MIND Foundation's psychedelic therapy training APT comes in
Training is the point at which TAIP and the MIND Foundation actually touch. TAIP's earlier scholarship holders trained in the OPEN Foundation's ADEPT program in the Netherlands and in our Augmented Psychotherapy Training (APT); several of them will share their experience on a panel at TAIP's conference on October 8 (TAIP, n.d.-c). On November 7, two TAIP-co-funded, Estonian professionals will join the ninth international APT cohort in Berlin. Their places are co-funded by TAIP, and for one of them the MIND Foundation is co-funding through one of our scholarships as well, each organization carrying a quarter of the tuition. Two organizations in two countries invest together in one professional who will, in a few months or years, treat patients and train colleagues in Estonian.
Why does the APT fit an ecosystem like this? Because it was built for it. The program has been international from its first cohort: around two hundred alumni from more than thirty-five countries as of 2026. The ninth cohort, starting November 7, 2026, is again taught in English, for professionals who return to their own health systems and stay connected through the APT alumni network. The tenth cohort, starting March 14, 2027, will be taught in German, for colleagues working in German-speaking health systems. It is oriented toward results that exist in the real world now: the curriculum is substance-unspecific, so that breathwork- and ketamine-augmented psychotherapy can be practiced under current law, and the same twelve competencies transfer to psilocybin and other classical psychedelics as they reach the clinic. Two hundred of its 360 units take place in person in Berlin, in an experience not reducible to a screen: with clinical experts and researchers, patients and patient actors, and clinicians from OVID Clinics. These clinicians do not only offer psychedelics as an addition to outpatient psychotherapy; they work across a whole spectrum of treatment settings, up to a day clinic delivering multimodal complex therapy. And it was never designed to serve a bubble: starting with this cohort on November 7, 2026, members of the MIND Lived Experience Group, founded in 2026, teach alongside the faculty, and the admission interview sorts applicants into a clinical-leadership or a collaborative-roles track before anyone pays.
The FDA's July guidance now spells out for the United States what a lead monitor and an assistant monitor must have studied and practiced (U.S. Food and Drug Administration, 2026a). Europe will not get a document like that from one agency yet. It gets, instead, a psychiatrist in Tallinn who trained with MAPS and Fluence, a foundation that co-funds the training of more professionals, and a program in Berlin whose faculty includes clinicians running psychedelic treatments inside the German healthcare system and a large variety of teachers from different angles, universities, and clinics from all over the world. On October 8, 2026, MIND Foundation co-founder Andrea Jungaberle will speak in Tallinn about five years of her clinical work at OVID Clinics – the challenges and successes that come with that. This is what a European "movement" looks like when you stop looking for its headquarters: a network with a strong German node, and several strong ones in other European countries, and new ones in places the maps of the field still leave blank.
What makes us Europeans
In their own words: year ten
Henrik Jungaberle: MIND Foundation is turning ten, so I give the question back to you. What would success look and feel like in TAIP's tenth year?
Cristina Kroon: According to our strategic plan, by then we will have been resting for a long time, because our job is done (laughing). We plan to achieve a lot by 2030 and then take a collective holiday. The big question is the same as everywhere: access. We now see more ketamine-assisted psychotherapy being offered, but the way it is going, it will only exist in private practices, and that is cost-prohibitive for the average patient. If we can expand access to ketamine in combination with psychotherapy, that would be huge.
Oliver Berg: If I fast-forward ten years and dream big: next to ketamine, we have psilocybin- and MDMA-assisted therapies that are publicly reimbursed, in a group therapy setting. Something that seemed a distant dream has become tangible reality, and the fear and stigma are gone, not because we went down the hype roads, but because we stopped being afraid of the potential of these treatments. Right now we put our energy into an egalitarian system in which people have access regardless of income, and into education: our first course was in September, an introductory course on ketamine-assisted therapy follows. Perhaps in ten years TAIP's focus is no longer lobbying but training the therapists who provide these treatments.
Henrik Jungaberle: In your own language, too, which will become necessary at some point. If we hadn't started as an English-speaking organization in Berlin and had held more of our debates in German, we would have been quicker in some respects. It took us time to realize this mistake, until we began speaking German again to our audiences.
Cristina Kroon: If you want a bigger statement: in ten years I hope we have started to turn the tide of mental health problems, which so far only grow. Not all of that will be due to psychedelic-assisted therapies. But maybe we will see slight decreases among the most treatment-resistant patients, and options for people with substance use disorders, which are huge public health problems in Estonia. Success would be contributing to that little turnaround.
That is a European answer, not a universal one. The question is not which company brings which molecule to market first. It is whether a treatment can be delivered by trained people, inside mixed public-private health systems, to the patients who need it most, in their own language. TAIP's ten-year ambition is to spend less time lobbying and more time training therapists in Estonian.
Cristina Kroon's hope that ketamine combined with psychotherapy should not remain a privilege of private practice already has a working precedent in the Nordic neighborhood. In August 2025, Norway became the first country to reimburse off-label racemic ketamine for treatment-resistant depression nationwide through its public health service, free of charge for patients, after a health technology assessment by the national medicines agency had found it more effective than its comparators at substantially lower cost (Nye metoder, 2025; Stewart et al., 2026). The model grew out of Scandinavia's first public ketamine unit, opened at Østfold Hospital in 2020 with the physician Lowan Stewart among its co-founders; there, preparation, set and setting, and concurrent psychotherapy are preconditions for treatment. Reimbursement is tied to delivery within specialist mental health services and to data collection in registries or studies (Stewart et al., 2026). That is implementation and evidence generation in a single move, and a model that a country of 1.36 million could adapt.
What is shared is the conviction that access is a public matter, and the willingness to build platforms between organizations that make it so. At the end of our conversation I offered to connect TAIP with companies that run clinical studies, so that Estonia's first trials might come from its own ecosystem.
Part 2 of this European series is in preparation, and we are drawing a map as we go: which organizations in Europe are implementing rather than talking, in which countries, with which allies, and with which results. The map will be published and updated with each part of the series, and it will be read by the people who decide where trials, scholarships, and cooperation go next: the APT's roughly two hundred alumni in more than thirty-five countries, the readers of our newsletter, and the partners we bring to the table. The co-funding arrangement we tried with TAIP is open to other organizations, and so is a place in the research and compassionate-use data network described above.
If your organization belongs on the map, write to us at info@mind-foundation.org with the subject line "European Ecosystem Series."
About the people in this story
Oliver Berg is executive director and one of the three founders of the TAIP Foundation (Foundation for Therapeutic Advancement and Innovation with Psychedelics), an Estonian non-profit advocating for access to psychedelic-assisted therapies within public healthcare. His interest in the field comes from lived experience with depression as well as academic research; at the University of Amsterdam he focused his MA thesis on the implications of the ongoing psychedelic renaissance for EU drug policy. The idea behind TAIP rests on a strong belief in European democracy: as societies, we should explore new treatment options openly and responsibly, guided by science, patients' voices, and learning from the advances of other European countries. Portrait: Siim Vahur.
Cristina Kroon trained at Charité University Hospital in Berlin, where she completed her master's and PhD in medical neuroscience over nine years, with research on brain disorders such as depression and Alzheimer's disease and on the processes underlying neuronal growth. She works at the medical faculty of the University of Tartu as an innovation scout, supporting the translation of scientific discoveries into therapeutics and diagnostics, and serves as policy and strategy lead of the TAIP Foundation. Since moving to Estonia she has been an active science communicator, lecturing on the brain to non-scientific audiences. Portrait: Copyright Cristina Kroon.
Header image: the TAIP team, photographed by Silver Gutmann.
The interview with Oliver Berg and Cristina Kroon was conducted online on September 22, 2026. The questions shown are a selection of those asked; the answers have been edited for length and clarity and were reviewed by Oliver Berg and Cristina Kroon before publication.
Abbreviations
Public bodies, programs and technical terms used in this article, in alphabetical order.
Abbreviation
Full name
What it is
5-HT2A
Serotonin 2A receptor
The receptor in the brain through which classic psychedelics mainly act.
ADEPT
Training program of the OPEN Foundation
Psychedelic therapy training offered by the OPEN Foundation in the Netherlands.
APT
Augmented Psychotherapy Training
The MIND Foundation's 15-month international training in psychedelic-augmented psychotherapy: 360 units, 200 of them in person in Berlin.
BfArM
Bundesinstitut für Arzneimittel und Medizinprodukte (Federal Institute for Drugs and Medical Devices)
Germany's federal authority for medicines; it authorizes clinical trials and compassionate use programs.
CHMP
Committee for Medicinal Products for Human Use
The EMA's scientific committee; it adopts opinions on medicines, including eligibility for PRIME.
EMA
European Medicines Agency
The EU agency that evaluates and supervises medicines; its opinions are the basis for marketing authorization in the EU.
EPIsoDE
Name of a clinical trial
German multicenter trial of psilocybin in treatment-resistant depression, led by Gerhard Gründer; its protocol is the basis of the German compassionate use program.
EUDA
European Union Drugs Agency
The EU agency (formerly EMCDDA) that monitors drug use and drug policy in Europe and publishes the annual European Drug Report.
FDA
U.S. Food and Drug Administration
The US federal agency that approves medicines and issues guidance for clinical trials.
The highest decision-making body of Germany's self-governing health system; it decides on added benefit and coverage, based on IQWiG assessments.
GDP
Gross domestic product
The total value of goods and services a country produces in a year.
HAS
Haute Autorité de Santé (French National Authority for Health)
France's independent HTA body; it rates the added clinical benefit of new treatments as a basis for pricing and reimbursement.
HTA
Health technology assessment
Systematic evaluation of whether a new treatment offers added benefit over existing care, and at what cost; the basis for reimbursement decisions.
HTA Regulation
Regulation (EU) 2021/2282 on health technology assessment
Since January 2025, it pools the clinical part of HTA at EU level in joint clinical assessments.
IQWiG
Institut für Qualität und Wirtschaftlichkeit im Gesundheitswesen (Institute for Quality and Efficiency in Health Care)
Independent German institute that assesses the benefit of treatments on behalf of the G-BA.
IV
Intravenous
Administered directly into a vein.
MAPS
Multidisciplinary Association for Psychedelic Studies
US nonprofit research and education organization that developed MDMA-assisted therapy and a related therapist training.
MDD
Major depressive disorder
The clinical diagnosis of depression.
MDMA
3,4-Methylenedioxymethamphetamine
A substance studied in combination with psychotherapy, mainly for posttraumatic stress disorder.
NGO
Non-governmental organization
A civil society organization independent of government.
NICE
National Institute for Health and Care Excellence
The HTA and clinical guideline body for England; outside the EU.
OECD
Organisation for Economic Co-operation and Development
Intergovernmental organization of 38 member countries that compares economic, social and health data.
OPEN Foundation
–
Dutch foundation in Amsterdam for interdisciplinary psychedelic research, education and training.
PAREA
Psychedelic Access and Research European Alliance
European alliance working for access to psychedelic therapies and research; legally registered in Estonia.
PRIME
PRIority MEdicines
EMA scheme offering early, enhanced support for medicines that address unmet medical needs; the European counterpart of the FDA's breakthrough therapy designation.
TAIP
Sihtasutus Teraapia Arenduseks ja Innovatsiooniks Psühhedeelikumidega (Foundation for Therapeutic Advancement and Innovation with Psychedelics)
Estonian foundation, registered in Tallinn in 2024, working for patients' access to psychedelic medicines.
ZI
Zentralinstitut für Seelische Gesundheit (Central Institute of Mental Health)
Psychiatric research institute and hospital in Mannheim; one of the two sites of the German psilocybin compassionate use program.
Butlen-Ducuing, F., McCulloch, D. E. W., Haberkamp, M., Mattila, T., Bałkowiec-Iskra, E., Aislaitner, G., Balabanov, P., Lundberg, J., Stenbæk, D. S., Elferink, A., Knudsen, G. M., & Thirstrup, S. (2023). The therapeutic potential of psychedelics: The European regulatory perspective. The Lancet, 401, 714–716. https://doi.org/10.1016/S0140-6736(23)00264-7
Gründer, G., Mertens, L. J., Jungaberle, A., Jungaberle, H., & Spangemacher, M. (2025). Compassionate use of psilocybin for treatment-resistant depression in Germany. The Lancet Psychiatry. Advance online publication. https://doi.org/10.1016/S2215-0366(25)00277-9
Gründer, G., Mertens, L. J., Spangemacher, M., Meyer-Lindenberg, A., & Jungaberle, H. (2026). Psychedelics: The pathway to implementation in the European healthcare systems. European Neuropsychopharmacology, 102, 41–48. https://doi.org/10.1016/j.euroneuro.2025.11.007
{+OECD. (2021). A new benchmark for mental health systems: Tackling the social and economic costs of mental ill-health (OECD Health Policy Studies). OECD Publishing. https://doi.org/10.1787/4ed890f6-en+}
Stewart, L. H., Berthold-Losleben, M., Kvam, T.-M., Lien, L., Andreassen, O. A., & Clausen, I. (2026). Transforming treatment-resistant depression care in Norway: Public health reimbursement for off-label intravenous ketamine. Drug Science, Policy and Law, 12. https://doi.org/10.1177/20503245261452347
U.S. Food and Drug Administration. (2026a). Psychedelic drugs: Considerations for clinical investigations – Guidance for industry. https://www.fda.gov/media/169694/download